Ask three surgeons what proportion of a fat graft survives and you will get three numbers, all of them defensible, none of them transferable to the case in front of you. That is not a failure of the literature. It is a clue about where retention is actually decided — and it is not decided at the moment of injection.
This article is about the chain of events a grafted adipocyte has to survive, and about which links in that chain are under the surgeon’s control. It is written for colleagues who already graft fat and want to reason about why a particular case underperformed.
The only hard constraint: diffusion
For the first days after transfer, a grafted parcel has no blood supply of its own. It lives on plasmatic imbibition — nutrients reaching it by diffusion from the surrounding tissue. Diffusion is not negotiable and it is not improved by technique, by processing, or by enthusiasm. It falls away with distance, and it does so steeply.
Everything that follows is a consequence of that single fact.
A parcel whose centre lies beyond the reach of diffusion does not partially survive. The rim takes and the core does not, and what the core becomes is fat necrosis: first an oil cyst, then, often enough, a palpable lump that brings the patient back for imaging and sometimes for biopsy. The complication is not a rare accident. It is the predictable result of a geometry that was chosen at the moment of injection.
This is why the surface-area-to-volume ratio of the parcel matters more than the total volume transferred. Distributing the same quantity of fat as many small deposits rather than a few large ones changes nothing about the amount of tissue involved and everything about how much of it lies within diffusion distance of a living wall.
Four links, and only some of them are yours
It is tempting to treat retention as a single variable. It is more useful to treat it as a chain, because a chain tells you where to look when the result disappoints.
Harvest. Adipocytes are fragile and shear is what kills them. Cannula diameter, the vacuum applied, and how roughly the tissue is handled all determine how much of what comes out of the donor site is intact cells rather than free oil and debris. A graft that was damaged at harvest cannot be rescued by anything done afterwards.
Processing. The aim is to remove blood, tumescent fluid, free lipid and cellular debris while preserving the adipocytes and the stromal vascular fraction that will drive revascularisation. Aggressive processing achieves the first half at the cost of the second. Our article on fat processing and graft quality goes into the trade-offs between decanting, centrifugation and washing systems, and fat dialysis describes one approach to the problem.
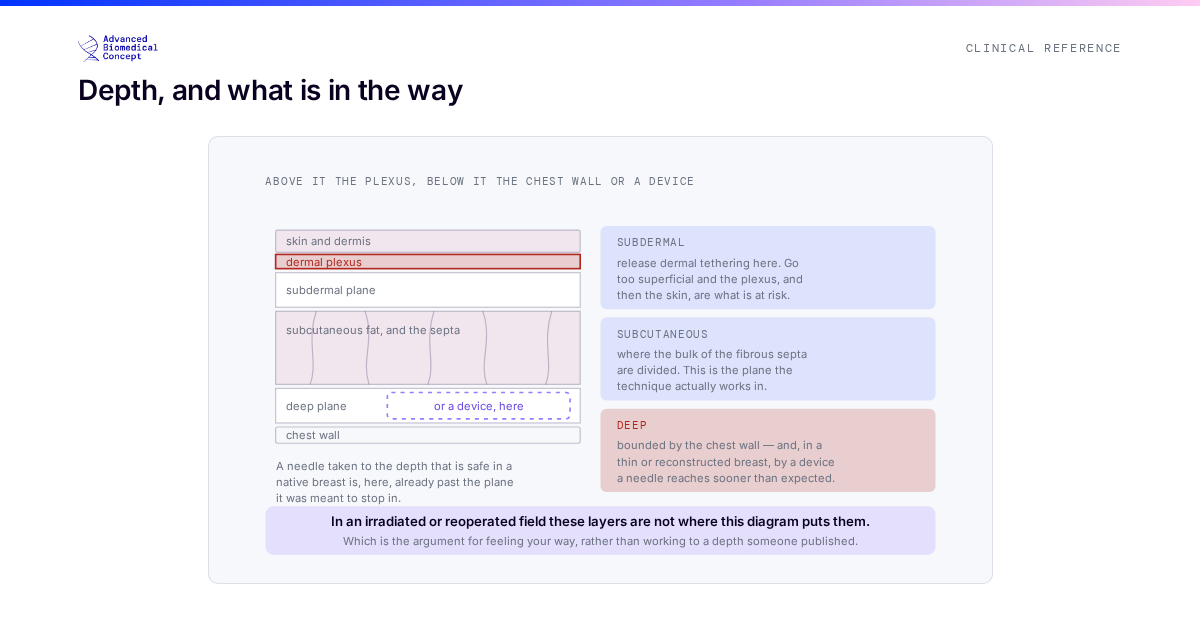
The recipient bed. This is the link most often treated as a given and it is the one with the most room in it. A bed that is scarred, irradiated, thin or fibrotic has fewer vessels per unit volume and less compliance, which means both a worse blood supply and less space to distribute fat into without raising interstitial pressure. Changing that bed is exactly what rigottomy is for.
Placement. Parcel size, pass geometry, the plane worked in, and how much is delivered per pass. This is the link with the most technique literature attached to it and, arguably, the least residual uncertainty: the principles of structural grafting are well established and widely taught.
The clinical value of laying the chain out this way is diagnostic. A disappointing result in a soft, well-vascularised, never-operated bed points at harvest, processing or placement. The same result in an irradiated chest wall points at the bed, and no refinement of cannula technique will fix it.
Pressure is the quiet variable
Interstitial pressure connects the bed to the graft in a way that is easy to underestimate. Fat delivered into a tight compartment raises the pressure in that compartment; raised pressure narrows the very capillaries the graft depends on. The graft then competes with itself for perfusion.
The practical consequence is that the ceiling on what a bed will accept is not set by anatomy alone but by compliance, and compliance is modifiable. A released, compliant bed accepts more fat at a lower pressure than a tight one of the same volume. This is the mechanism behind recipient-site preparation, and it is covered in detail in rigottomy as recipient-site preparation.
What the evidence can and cannot tell you
Retention figures in the literature are difficult to compare because the studies differ in almost every respect that matters: how volume was measured (and whether it was measured at all, or estimated), at what interval, in which recipient site, after how many sessions, and with what processing. A series reporting a high retention rate in an unoperated breast is not evidence about an irradiated chest wall.
When reading a series, the questions that separate a useful paper from a quotable one are the ones in our guide to reading a breast reconstruction clinical study: what was measured, by whom, against what baseline, and over what period. Volumetric imaging and patient-reported measures such as those discussed in patient-reported outcomes and BREAST-Q answer different questions, and a paper that reports one should not be read as having answered the other.
Where this leaves the operative plan
If diffusion sets the constraint and the bed sets the ceiling, then the plan follows: assess the bed first, prepare it if it will not take what is needed, distribute finely, and accept that the volume achievable in one sitting may be less than the volume the defect requires. That last point is the subject of the companion article on planning fat grafting across sessions.
In reconstruction specifically, fat grafting rarely stands alone. It is used to refine contour over an implant, to thicken a thin mastectomy flap, to soften a radiotherapy field, and to correct the rippling and step-off that follow implant-based reconstruction — roles set out in prepectoral reconstruction with matrix and fat grafting and in reducing complications in implant-based reconstruction.
The short version
Retention is not a property of the fat. It is a property of the relationship between the fat and the space it was put into, and that relationship is largely decided before the syringe is loaded — by the bed the surgeon inherited, and by what was done to prepare it.
This article is educational material for clinicians. It describes principles and trade-offs, not a protocol, and it deliberately avoids quoting volumes, intervals or retention percentages: those are judgements about an individual patient and an individual tissue bed.
Important information This article is general education, not medical advice. Tap to read the full medical, regulatory & legal notice.
This article is provided by Advanced Biomedical Concept for general informational and educational purposes only. It does not constitute medical, surgical, diagnostic, or other professional healthcare advice, and it is not a substitute for consultation with a suitably qualified healthcare professional. Reading it creates no doctor–patient or other professional relationship. Nothing here should be used to diagnose, treat, cure, or prevent any disease or condition, or to make decisions about medical care. Always seek the advice of a physician or other qualified provider with any questions about a medical condition or treatment, and never disregard or delay professional advice because of something you have read here.
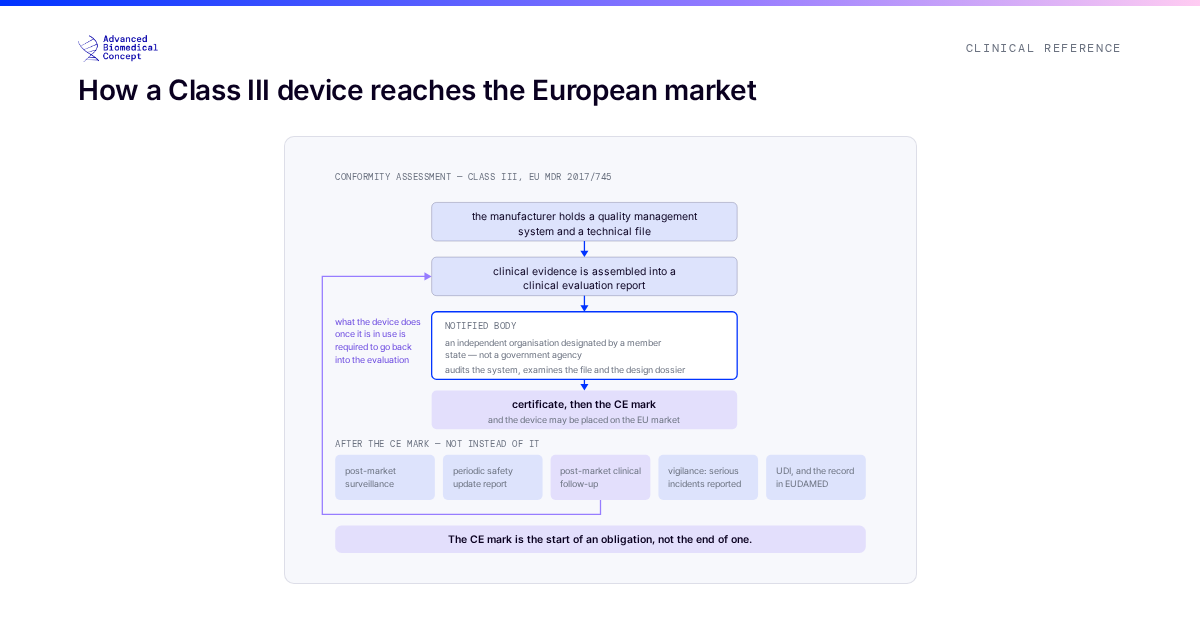
Any reference to Advanced Biomedical Concept products (including ExaShape and ExaFat) is provided for general information only. These are medical devices intended to be used by appropriately trained healthcare professionals strictly in accordance with their applicable, current Instructions for Use (IFU). Regulatory status (including CE marking and classification under the EU Medical Device Regulation), market availability, and approved indications differ between countries and may change over time; a device referred to here may not be available or approved in your country. This content is not intended as, and must not be relied upon as, a statement or claim of safety, clinical performance, or efficacy beyond what is set out in the applicable IFU and current regulatory approvals. Product-specific information is directed at healthcare professionals and is not intended to promote, advertise, or offer any medical device to the general public where such promotion is restricted or prohibited by law.
Statements reflect information believed to be accurate at the date of publication and may be updated or corrected without notice. Any statements regarding the future are expectations or general views, not guarantees. Clinical outcomes depend on many individual factors, results vary from person to person, and no particular result is promised or implied. Where third-party studies, sources, or external links are referenced, they are provided for convenience and information only and do not imply endorsement, and Advanced Biomedical Concept is not responsible for their content.
To the fullest extent permitted by applicable law, Advanced Biomedical Concept and its officers, employees, contributors, and representatives (each acting in that capacity and on behalf of Advanced Biomedical Concept) accept no liability for any loss, injury, or damage of any kind arising directly or indirectly from use of, or reliance on, this content. Nothing in this notice excludes or limits any liability that cannot lawfully be excluded or limited.
Questions about this material can be directed to us via our contact page.
Last reviewed: September 25, 2026.