Two questions decide whether a percutaneous release is safe in a reconstructed or irradiated chest: how deep, and when. Neither has a published answer that can be applied to a patient, and both have answers that can be reasoned about carefully.
Depth: what is at each level, and what is in the way
The technique works in the subcutaneous plane, dividing fibrous septa. Too superficial and the dermal plexus is at risk, and the skin with it. Too deep and the chest wall — or, in a reconstructed breast, the device — is closer than the mental model suggests.
The dermal plexus deserves its own line in that diagram rather than being drawn as a boundary, because it behaves as a layer with thickness that the needle can be inside. Working immediately beneath the dermis in an attempt to release surface tethering is precisely where it is compromised, and the consequence — skin compromise in tissue that is already thin and often already irradiated — is considerably worse than the tethering that prompted it.
At the other end, a reconstructed breast has a device in it. In a prepectoral reconstruction that device is in front of the muscle, closer to the skin than anatomical intuition expects, and separated from the needle by whatever the mastectomy left behind. In a thin flap that can be very little. An implant puncture during what was planned as a minor refinement procedure means explantation, and possibly the loss of the reconstruction.
The prepectoral geometry is described in plane selection in direct-to-implant reconstruction, and it changes this calculation directly: the plane the surgeon must not reach is nearer than in a subpectoral reconstruction.
Why the drawing cannot carry millimetres
The diagram above names the layers in order. It does not say how thick they are, and that is deliberate rather than an omission. In an irradiated, reoperated or reconstructed field the layers are not where a textbook section puts them. Fibrosis obliterates planes, previous surgery has moved them, and the mastectomy has removed most of one.
Which is the argument for tactile control — feeling the resistance change as bands divide, rather than working to a depth someone published in a different patient.
Timing: the interval after radiotherapy
The second question is when, and here the honest answer is that the interval is a judgement about tissue rather than a date on a calendar.
During and immediately after radiotherapy the tissue is acutely inflamed, the skin is fragile and healing is impaired. Nothing elective belongs in that period. Once the acute reaction settles, the tissue enters a phase in which radiation fibrosis develops — and the key point, the one the figure is drawn to make, is that fibrosis keeps developing. It does not stop when the treatment stops.
That has two consequences that pull in opposite directions. Operating too early means operating on tissue that is still acutely damaged. Operating later means operating on tissue that is more fibrotic than it was — and progressively more difficult to release and less able to support a graft.
There is therefore a window, and its boundaries are clinical: the acute reaction has settled, the skin has recovered, the tissue is stable enough to assess, and the fibrosis has not yet become the dominant problem. Assessing that means examining the patient, not counting months.
Oncology sets the timetable
The sequencing decision is not the reconstructive surgeon’s to make alone, and the order of precedence is not negotiable: the oncological plan comes first and reconstruction fits around it. A reconstruction scheduled in a way that delays or compromises adjuvant treatment is the wrong reconstruction regardless of its technical merit.
This is also why the sequencing question has to be settled before the technique question is worth discussing. Radiotherapy and breast reconstruction covers the wider interaction, and the oncologic pathway sets out where these decisions sit in the overall course of treatment.
Whether to release at all
Before depth and timing comes a question that is easier to skip: is this tissue a candidate. Not every irradiated chest wall should be released, and the features that make a field difficult are the same ones that make it risky.
Skin quality is the first filter. Telangiectasia, atrophy, pigmentary change and a dermis that has lost its thickness all indicate a field in which a needle passed superficially will do more harm than the tethering it was aimed at. Ulceration or a non-healing area is a contraindication rather than an indication, however tempting it is to treat it as a target.
The second is whether there is anything to release into. Release creates space; the graft needs a vascularised wall around that space. A field so fibrotic and so poorly perfused that it will not support a graft is not made suitable by making it compliant — it is made compliant and still unsuitable, with a fresh set of cavities that fill with blood or with fat that does not take.
The third is the patient’s own position. A staged plan in irradiated tissue is likely to be a long one, and a patient who is expecting a single corrective procedure has not consented to what is actually proposed. That conversation belongs before the first operation, not between the second and third.
Release in an irradiated field behaves differently
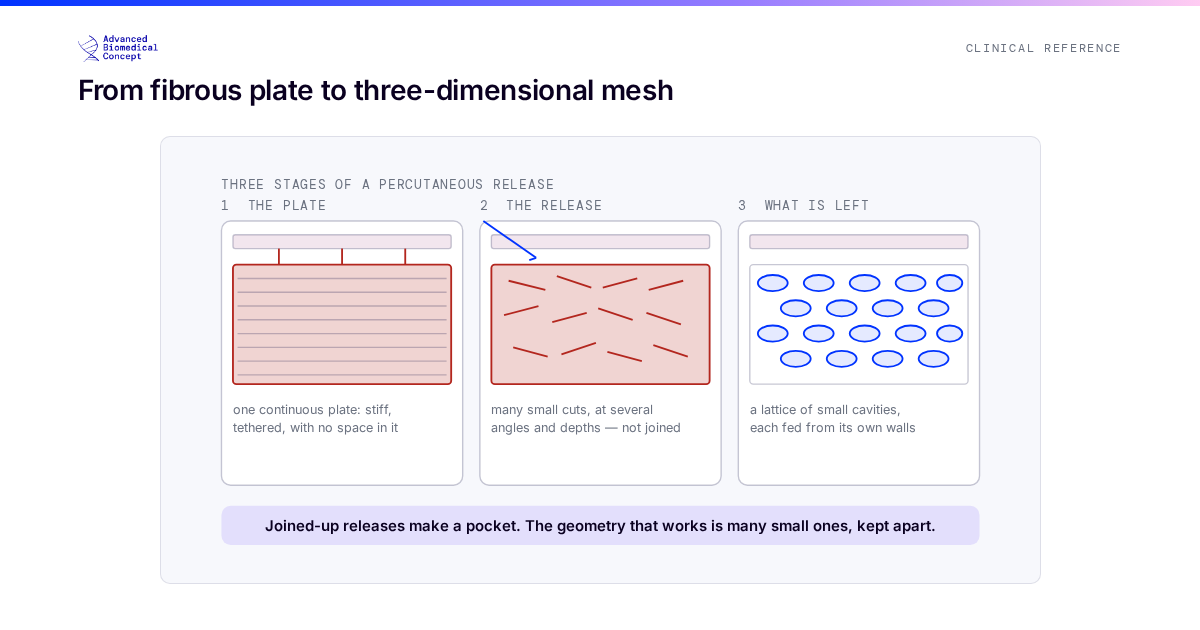
Three differences matter at the table. Irradiated tissue is less compliant, so the same release achieves less and the temptation to be more aggressive is correspondingly greater — which runs directly into the macrocavity problem described in release mechanics and macrocavity avoidance. It is less vascular, so the released bed supports a smaller graft volume and more sessions are likely. And it is less forgiving of skin compromise, so the superficial limit is nearer than usual.
All three point the same way: smaller steps, more of them, and a plan that assumes staging from the outset, as set out in planning fat grafting across sessions.
The short version
Depth is controlled by feel, not by a number, because in this field the layers are not where diagrams put them. Timing is a window defined by how the tissue is behaving, not by an interval, and the window sits inside a timetable that oncology owns.
This article is educational material for clinicians. No depths and no intervals are given, because both are assessments of an individual patient’s tissue and neither would be safe to transfer from a website to a theatre.
Important information This article is general education, not medical advice. Tap to read the full medical, regulatory & legal notice.
This article is provided by Advanced Biomedical Concept for general informational and educational purposes only. It does not constitute medical, surgical, diagnostic, or other professional healthcare advice, and it is not a substitute for consultation with a suitably qualified healthcare professional. Reading it creates no doctor–patient or other professional relationship. Nothing here should be used to diagnose, treat, cure, or prevent any disease or condition, or to make decisions about medical care. Always seek the advice of a physician or other qualified provider with any questions about a medical condition or treatment, and never disregard or delay professional advice because of something you have read here.
Any reference to Advanced Biomedical Concept products (including ExaShape and ExaFat) is provided for general information only. These are medical devices intended to be used by appropriately trained healthcare professionals strictly in accordance with their applicable, current Instructions for Use (IFU). Regulatory status (including CE marking and classification under the EU Medical Device Regulation), market availability, and approved indications differ between countries and may change over time; a device referred to here may not be available or approved in your country. This content is not intended as, and must not be relied upon as, a statement or claim of safety, clinical performance, or efficacy beyond what is set out in the applicable IFU and current regulatory approvals. Product-specific information is directed at healthcare professionals and is not intended to promote, advertise, or offer any medical device to the general public where such promotion is restricted or prohibited by law.
Statements reflect information believed to be accurate at the date of publication and may be updated or corrected without notice. Any statements regarding the future are expectations or general views, not guarantees. Clinical outcomes depend on many individual factors, results vary from person to person, and no particular result is promised or implied. Where third-party studies, sources, or external links are referenced, they are provided for convenience and information only and do not imply endorsement, and Advanced Biomedical Concept is not responsible for their content.
To the fullest extent permitted by applicable law, Advanced Biomedical Concept and its officers, employees, contributors, and representatives (each acting in that capacity and on behalf of Advanced Biomedical Concept) accept no liability for any loss, injury, or damage of any kind arising directly or indirectly from use of, or reliance on, this content. Nothing in this notice excludes or limits any liability that cannot lawfully be excluded or limited.
Questions about this material can be directed to us via our contact page.
Last reviewed: September 25, 2026.